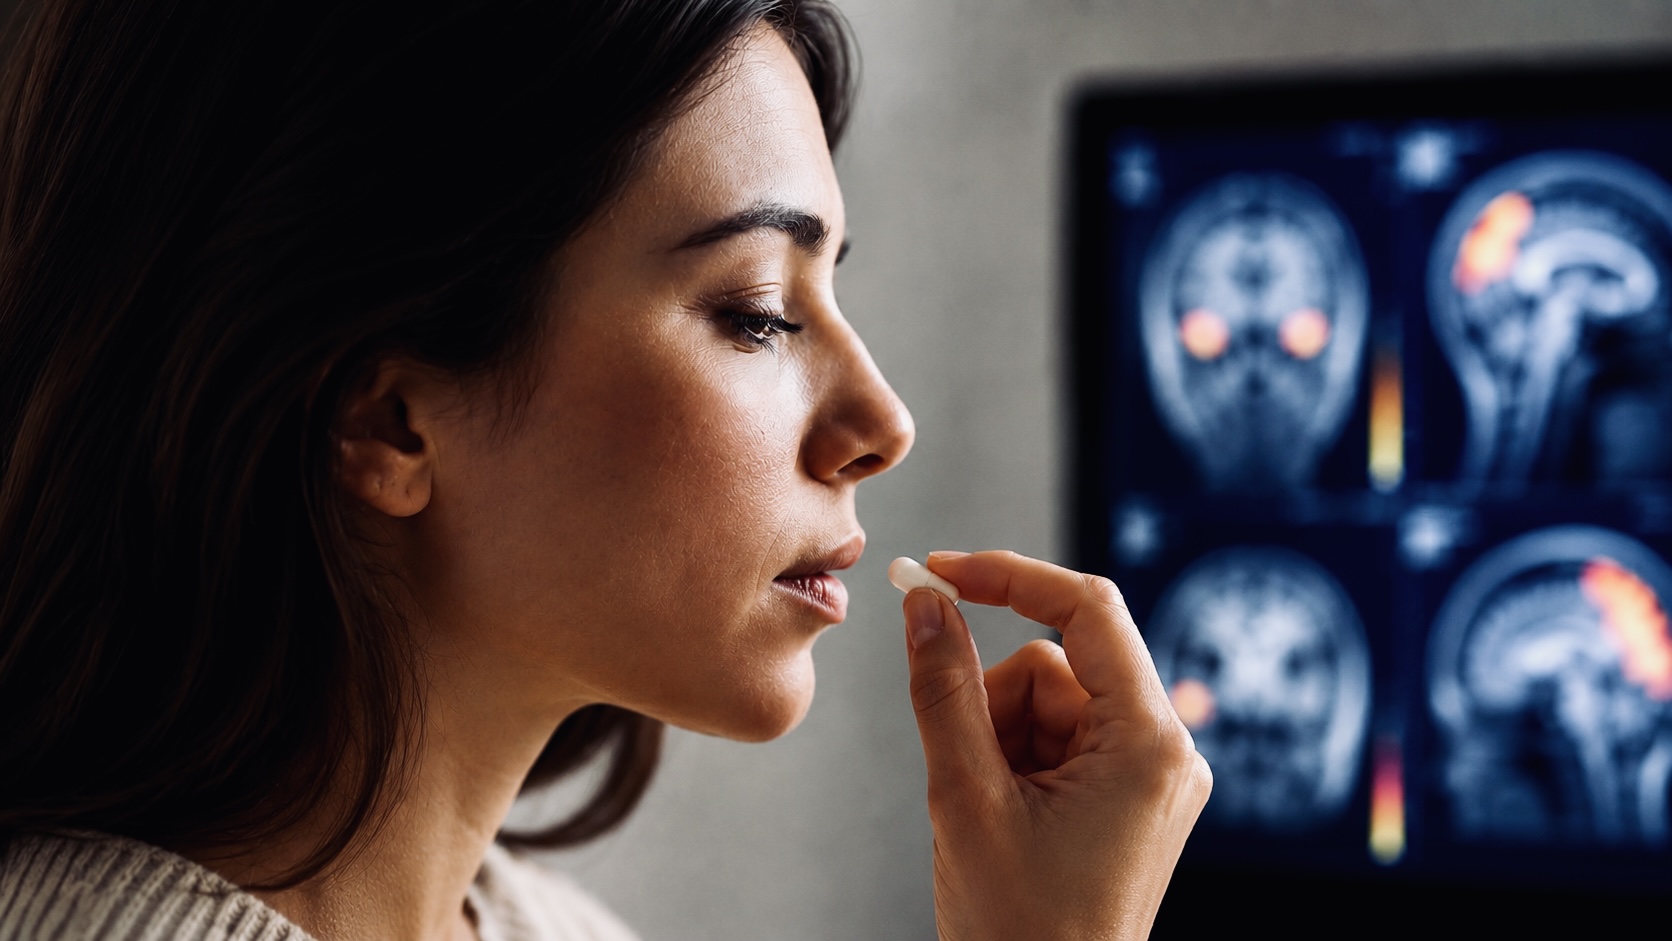
A placebo may contain no active drug, yet the response it triggers can be biologically real. Research has shown that expectations, previous experiences and the context surrounding medical treatment can influence pain, symptoms and activity within brain systems involved in reward and pain control.
The placebo effect is therefore not simply a patient imagining that they feel better. But neither is it evidence that the mind can cure any illness through positive thinking. Its effects vary considerably among people and conditions, and the strongest evidence concerns symptoms such as pain rather than eliminating the underlying cause of a disease.
That distinction helps explain why placebo research has become important not only for understanding the brain, but also for designing clinical trials and understanding why the experience of receiving treatment can influence its outcome.
What Placebo Does Inside the Brain
A placebo is usually an inactive intervention designed to resemble a treatment. The placebo effect refers to changes associated with the treatment context rather than the specific pharmacological action of a drug.
Expectation is one important mechanism. Past treatment experiences, instructions from health professionals, learned associations and the clinical environment can all influence what the brain anticipates will happen. Those expectations can then alter how symptoms are processed.
Pain provides some of the clearest evidence.
Research on placebo analgesia has implicated the body’s endogenous opioid system, the brain’s own pain-modulating chemistry. Neuroimaging studies have also identified involvement of brain networks associated with pain, emotion, expectation and reward. The International Association for the Study of Pain notes that expectation can influence pain processing and, under experimental conditions, even alter transmission of pain-related signals in the spinal cord.
Dopamine provides another example. Research involving Parkinson’s disease has found that expectation of benefit can be associated with dopamine release in the striatum, a brain region strongly affected by the disease. That does not mean placebo treatment reverses Parkinson’s disease; rather, it demonstrates that treatment expectations can engage measurable neurochemical processes.
More recent laboratory research is adding detail to the picture. A 2024 study highlighted by the U.S. National Institutes of Health identified a neural circuit involved in expectation-driven placebo pain relief in mice. Because the work was conducted in animals, it cannot by itself establish that precisely the same pathway operates in humans, but it offers researchers another potential mechanism to investigate.
Placebo effects also have a negative counterpart. A nocebo effect occurs when negative expectations contribute to worse symptoms or perceived side effects. This is one reason the way risks and treatments are communicated can matter clinically without making the underlying illness psychological or imaginary.
Why Placebos Have Important Limits
Perhaps the most important misconception is that a placebo response and a cure are the same thing.
They are not.
A person can experience genuine symptom improvement without the underlying disease being eliminated. Pain, nausea, fatigue and other experiences are influenced by neural processing, making them particularly susceptible to contextual and expectation effects. Changing those symptoms does not necessarily remove an infection, destroy a tumour, repair damaged tissue or correct another underlying biological cause.
Placebo responses also should not be confused with every improvement seen in a placebo group during a clinical trial. Symptoms can fluctuate naturally, illnesses can improve over time, patients can change other behaviours and measurements can vary. Researchers must separate these influences as carefully as possible when determining whether an experimental treatment actually works.
This is one reason placebo-controlled trials remain an important tool in medicine. The U.S. Food and Drug Administration describes a placebo concurrent control as comparing an experimental treatment with an inactive preparation designed to resemble it, typically using randomization and blinding. Ethical considerations can limit placebo use when withholding an established effective treatment could harm participants.
The comparison helps researchers determine whether an experimental therapy provides benefits beyond the effects associated with receiving treatment, expectations and other changes occurring during a trial.
There is also an intriguing variation: the open-label placebo.
In these studies, participants are explicitly told that they are receiving a placebo. A systematic review and meta-analysis published in Scientific Reports found evidence of beneficial effects across the randomized trials it examined, even without deception. However, the researchers emphasized important limitations, including relatively small studies, differences among trials and potential biases. The findings therefore do not establish open-label placebos as substitutes for proven medical treatment.
The larger lesson from placebo science is more nuanced than the idea that people can simply “think themselves better.”
The brain is part of the body, and expectations, learning and treatment context can interact with biological systems capable of changing how symptoms are experienced. Those mechanisms may eventually help clinicians improve how effective treatments are delivered and reduce harmful nocebo responses.
But recognizing the biological power of expectation also requires recognizing its boundaries. Placebo research demonstrates that the experience of treatment can matter. It does not erase the distinction between feeling better and treating the biological cause of disease.
About the Author Brad Socha is the founder of The Universal Record, focused on sourced, factual global reporting. Coverage includes international news, geopolitics, technology, and major developments.